The problem
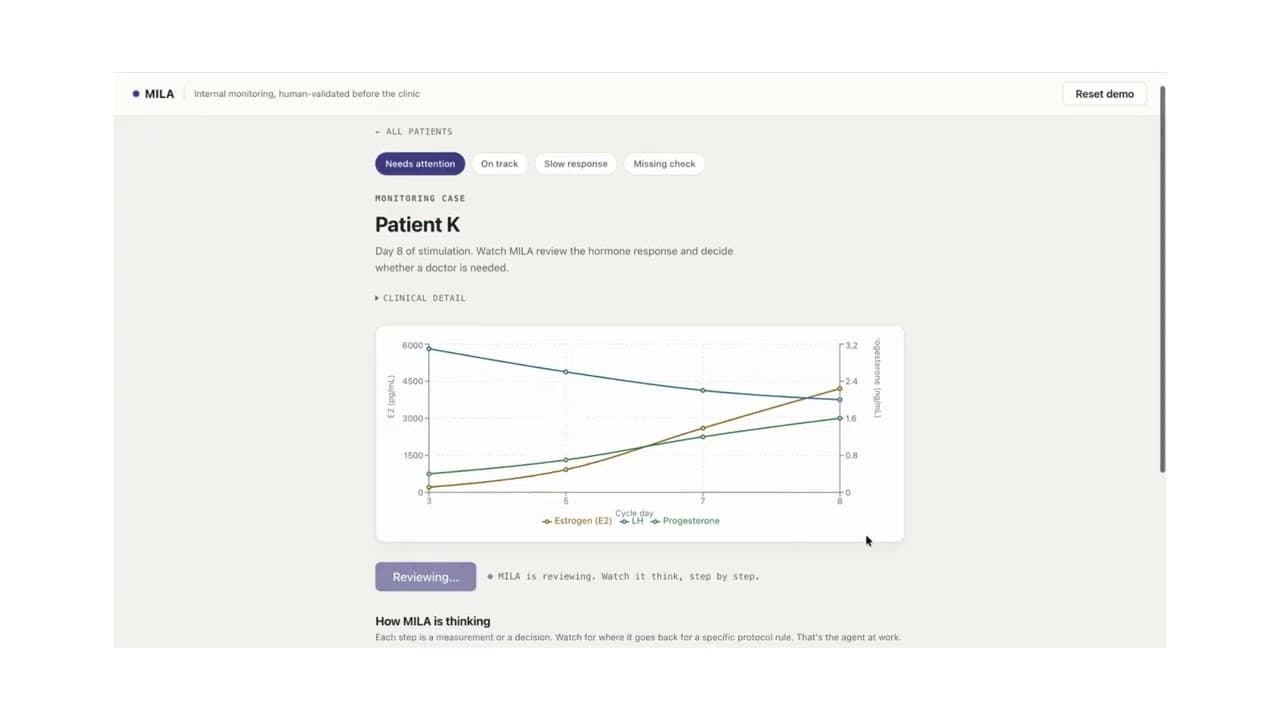
During an IVF stimulation cycle, a patient is monitored every 24–48 h with serial hormone draws (estradiol, LH, progesterone) and follicle scans. A clinician writes a follow-up instruction — "repeat this within 24 h", "watch the progesterone", "she's a high responder" — and then the cycle moves fast. Records fragment across the lab system, the scan report and the clinician's note. The single most time-critical complication, OHSS (Ovarian Hyperstimulation Syndrome), announces itself precisely in the trajectory: a steep estradiol rise per day, a high estradiol-per-follicle, PCOS. Miss the window and it becomes an emergency.
The failure mode isn't a lack of data — it's that nobody rebuilds the trajectory, checks it against the protocol, and raises the flag in time.
The idea
For every new serial result, Mila:
rebuilds the patient's hormone trajectory from her fragmented records,
runs deterministic calculators (rate-of-rise, OHSS composite, progesterone-for-cycle-day, response-curve…),
conditionally retrieves the governing protocol/SOP article — only the one the computation calls for,
drafts a cited monitoring brief with an escalation flag,
and hands it to a human biologist to validate before anything reaches the clinic.
It answers one operational question — never a clinical one:
Is there sufficient documented evidence that the requested follow-up was completed, and if not, what workflow task should staff review next?
It does not diagnose, interpret whether a value is medically abnormal, recommend treatment, or prescribe. The LLM proposes; deterministic code disposes.
Note: the demo URL is substituted with the GitHub repository link.